 KSOEM


Articles
- Page Path
- HOME > Ann Occup Environ Med > Volume 38; 2026 > Article
- Original Article Association between urinary bisphenol levels and metabolic syndrome in Korean adults: a cross-sectional study using the fourth Korean National Environmental Health Survey
-
Chang Ho Jae
 , Young Hoo Shin*, Chang Ho Chae, Chan Woo Kim, Hyoung Ouk Park, Yong Tae Park, Dae Yeon Kang
-
Annals of Occupational and Environmental Medicine 2026;38:e36.
DOI: https://doi.org/10.35371/aoem.2026.38.e36
Published online: July 27, 2026
Department of Occupational and Environmental Medicine, Samsung Changwon Hospital, Sungkyunkwan University School of Medicine, Changwon, Korea
- *Correspondence: Young Hoo Shin Department of Occupational and Environmental Medicine, Samsung Changwon Hospital, Sungkyunkwan University School of Medicine, 158 Paryong-ro, Masanhoewon-gu, Changwon 51353, Korea E-mail: bonjoviz@naver.com
• Received: April 30, 2026 • Revised: July 13, 2026 • Accepted: July 15, 2026
© 2026 Korean Society of Occupational & Environmental Medicine
This is an Open Access article distributed under the terms of the Creative Commons Attribution Non-Commercial License (https://creativecommons.org/licenses/by-nc/4.0/) which permits unrestricted non-commercial use, distribution, and reproduction in any medium, provided the original work is properly cited.
- 1,312 Views
- 29 Download


Abstract
-
Background Bisphenols are representative endocrine-disrupting chemicals and have shown an association with metabolic disorders. Although the use of alternative bisphenols such as bisphenol F (BPF) and bisphenol S (BPS) has been increasing while that of bisphenol A (BPA) has been declining, limited population-based studies exist in Korea examining the association between these substances and metabolic syndrome (MetS). Therefore, this study aimed to evaluate the association of urinary BPA, BPF, and BPS concentrations with MetS in South Korean adults using data from the fourth Korean National Environmental Health Survey (KoNEHS).
-
Methods This study included 2,639 participants from the 2018–2019 KoNEHS. MetS was defined based on the modified National Cholesterol Education Program Adult Treatment Panel III criteria. The fasting blood glucose criterion was replaced with glycated hemoglobin (HbA1c) (≥5.7% or medication use). Urinary BPA, BPF, and BPS concentrations were categorized into tertiles per substance. Weighted binary logistic regression analysis accounting for the complex sampling design was performed to calculate odds ratio (OR) and 95% confidence interval (CI).
-
Results In the final adjusted model, urinary BPF concentration demonstrated a significant positive association with MetS, with ORs of 1.320 (95% CI: 1.029–1.693) for T2 and 1.452 (95% CI: 1.122–1.878) for T3. Urinary BPS concentration demonstrated a significant association only in the highest tertile, with an OR of 1.476 (95% CI: 1.067–2.043) for T3. Conversely, urinary BPA concentration did not show a significant association with MetS.
-
Conclusions In this study, urinary BPF and BPS concentrations in the general Korean adult population showed a significant positive association with MetS. The study findings may provide a baseline for expanding our understanding of the effects of bisphenols on health. Future long-term, prospective studies involving the general population remain necessary.
BACKGROUND
Metabolic syndrome (MetS) is a condition characterized by a combination of metabolic abnormalities such as elevated blood pressure, hyperglycemia, dyslipidemia, and obesity (particularly abdominal obesity), associated with an increased risk of cardiovascular disease and diabetes.1 Furthermore, MetS is closely associated with the development of various chronic diseases, including nonalcoholic fatty liver disease and chronic kidney disease.2,3 The global prevalence of MetS is high, with more than one-fifth of the adult population in the Asia-Pacific region affected.4 Among Korean adults, the prevalence increased from 27.1% in 2001 to 33.2% in 2020.5 This increase in prevalence has been suggested to be largely attributable to lifestyle changes, such as Westernized dietary habits and physical inactivity. Environmental chemicals, widely used in daily life, have also been identified as contributing factors to MetS development, due to disrupted metabolic and hormonal homeostasis.5,6
Endocrine-disrupting chemicals (EDCs) are exogenous substances that interfere with hormone synthesis, secretion, transport, metabolism, and receptor action, and have the potential to affect metabolic regulation and endocrine homeostasis in the human body.7 EDCs are widely present in myriad of consumer products and environmental media, resulting in frequent daily exposure in the general population. Bisphenols, a class of compounds containing two phenol rings, are representative examples. Bisphenols have been reported to disrupt hormonal signaling pathways and affect hormonal homeostasis and overall metabolism.8 Among these, bisphenol A (BPA), a synthetic phenol widely used in the manufacturing of polycarbonate plastics and epoxy resins, is found in a variety of applications, including food packaging, water pipes, can linings, and thermal paper.9 BPA exhibits high detection rates in human biomonitoring samples due to continuous exposure via ingestion and dermal absorption.10 Concerns regarding the health implications of BPA have led to an increased utilization of its alternatives, including bisphenol F (BPF) and bisphenol S (BPS). However, these substitutes have also raised concerns due to their structural similarity to BPA, which may result in comparable endocrine-disrupting activity and toxicological effects.11
Exposure to bisphenol may induce a multitude of health effects, including alterations in thyroid and immune function, metabolic and cardiovascular diseases, reproductive and developmental abnormalities, and behavioral and emotional changes.12 Since BPA shares structural similarities with the natural estrogen 17β-estradiol, it can act on estrogen receptors (ERs), thereby disrupting normal hormonal signaling.13 BPA also inhibits adiponectin release from adipose tissue, promotes adipocyte differentiation, and contributes to fat accumulation.14 These biological mechanisms may help explain the association between BPA exposure and several metabolic abnormalities, including insulin resistance, hyperglycemia, dyslipidemia, and obesity.15 Despite the paucity of evidence regarding the health effects of BPA analogs BPF and BPS compared to BPA, it is considered that these substances may also exhibit similar endocrine-disrupting effects, given that they share a common chemical structure, particularly the phenolic hydroxyl group.11
The Ministry of Environment and the National Institute of Environmental Research conducted the fourth Korean National Environmental Health Survey (KoNEHS) from 2018 to 2020, which included measurements of urinary BPA, BPF, and BPS concentrations. These data are valuable as nationwide biomonitoring data representative of the general population in South Korea. To date, no studies have examined the association of urinary BPF and BPS concentrations with MetS in Korean adults using domestic data. Therefore, this study aimed to evaluate the association of urinary BPA, BPF, and BPS concentrations with the prevalence of MetS among Korean adults using data from the fourth KoNEHS.
METHODS
This study was a secondary analysis of the raw data from the fourth KoNEHS (2018–2020). KoNEHS is a national survey conducted every 3 years since 2009 to assess exposure levels to environmental chemicals, their spatial and temporal distribution, trends over time, and associated factors. The sample was selected using stratified cluster sampling to ensure its representativeness of the Korean adult population. After stratifying the sample based on administrative districts and housing types, 245 primary sampling units were selected. In each sampling unit, 15 households were selected using systematic sampling, and all household members aged ≥ 19 years in the selected households were included in the survey. The survey consisted of questionnaire-based surveys, physical measurements, blood pressure measurements, and the collection and analysis of biological samples. Specialized survey teams visited the survey sites to collect data and manage the samples.
The fourth KoNEHS included a total of 4,239 adults aged ≥ 19 years (1,889 males and 2,350 females). Of these, 1,222 participants from the 2020 survey were excluded as their physical measurements, blood pressure readings, and blood samples were not collected due to the coronavirus disease 2019 (COVID-19) pandemic. Participants with missing data on measurements, laboratory tests, or questionnaire variables required for this study, including glycated hemoglobin (HbA1c), high-density lipoprotein (HDL) cholesterol, waist circumference, and blood pressure, were further excluded (n = 40). Before the final analysis, participants with urinary creatinine levels outside the normal range were also excluded (n = 338). Finally, 2,639 participants were included in the analysis (Fig. 1).
Although more than 20 bisphenol analogs have received considerable attention in research and regulatory circles,16 this study focused on three representative compounds: BPA, BPF, and BPS. The substances were separated and quantified using an API Triple Quad 5500 high-performance liquid chromatography-tandem mass spectrometry system (AB Sciex, Framingham, MA, USA). The method detection limits (MDLs) for each compound based on this test were 0.029 μg/L, 0.036 μg/L, and 0.022 μg/L for BPA, BPF, and BPS, respectively. For concentrations below the limit of detection, a value equal to the MDL divided by the square root of 2 was assigned.
MetS was defined in accordance with the clinical practice guidelines established by the Korean Society of Cardiometabolic Syndrome, employing the modified National Cholesterol Education Program Adult Treatment Panel III (NCEP ATP III) criteria. MetS was defined as the presence of ≥3 of the following five components: abdominal obesity (waist circumference ≥90 cm in men and ≥85 cm in women); elevated triglycerides (≥150 mg/dL); low HDL cholesterol (<40 mg/dL in men and <50 mg/dL in women); elevated blood pressure (systolic blood pressure ≥130 mmHg or diastolic blood pressure ≥85 mmHg or medication use); and elevated fasting blood glucose (≥100 mg/dL or medication use).17 However, since fasting blood glucose levels were not measured in the KoNEHS, this study applied an operational definition for MetS. In other words, based on the findings of previous studies reporting the use of HbA1c as a diagnostic criterion for MetS,18,19 the fasting blood glucose criterion was replaced with HbA1c (≥ 5.7% or medication use). An HbA1c level of ≥5.7% corresponds to the prediabetes criterion of the American Diabetes Association and has been suggested in previous studies to reflect a category of metabolic abnormality similar to that captured by the NCEP ATP III fasting blood glucose criterion of ≥100 mg/dL.
Face-to-face interviews were conducted to assess lifestyle habits and demographic characteristics, including age, sex, alcohol consumption, smoking status, physical activity, and education level. Participants were categorized into groups based on their responses, including on age (19–39, 40–59, or 60 years and older); alcohol consumption (never, less than once a month, or once a month or more); smoking status (non-smoker, former smoker, or current smoker); physical activity (none, moderate exercise without sweating, or vigorous exercise with sweating); and education level (less than high school, high school graduate, or university or higher). Urinary creatinine levels were included as a covariate to account for the diluting effect of urine.20
The general characteristics of participants in the non-MetS and MetS groups were assessed using frequencies and percentages. The representativeness of the nationwide sample was ensured by conducting all analyses using sample weights that reflect the complex sample design; however, the number of participants was not adjusted by applying these weights. Since the urinary bisphenol concentrations exhibited a non-normal distribution, a log transformation was applied during analysis, with the results presented as the geometric mean (GM) and geometric standard deviation (GSD). Given the potential nonlinear association with MetS, urinary BPA, BPF, and BPS concentrations were categorized into tertiles based on the distribution of each substance.21 The differences in the general characteristics between the non-MetS and MetS groups were compared using a chi-square test for categorical variables. The association between urinary bisphenol concentrations and MetS was examined using logistic regression analysis, and odds ratios (ORs) and 95% confidence intervals (CIs) were estimated. In the crude model, the association between urinary bisphenol concentrations and MetS was examined without adjustment for covariates. In model 1, age, sex, and urinary creatinine levels were included as covariates. In model 2, additional adjustments were made for alcohol consumption, smoking status, physical activity, and education level, in addition to model 1. The statistical analysis was performed using SPSS Statistics for Windows, version 26.0 (IBM Corp., Armonk, NY, USA), and the results were considered statistically significant for p < 0.05.
The present study protocol was reviewed and approved by the Institutional Review Board of Samsung Changwon Hospital (IRB No. 2026-04-019-001).
RESULTS
Table 1 presents the general characteristics of the KoNEHS participants included in this study. Of the 2,639 participants, 1,421 (53.85%) and 1,218 (46.15%) were categorized into the non-MetS and MetS groups, respectively. The age distribution differed significantly between the two groups (p < 0.001), with the MetS group having a higher proportion of participants aged ≥60 years and a lower proportion of those aged 19–39 years than the non-MetS group. The proportion of men was also higher in the MetS group (p = 0.001). The prevalence of overweight and obesity was significantly higher in the MetS group (p < 0.001). The two groups showed significant differences in smoking status and education level, with the MetS group having higher proportions of former or current smokers (p < 0.001) and a higher proportion of participants with lower education levels (p < 0.001). However, no significant differences were observed between the two groups in alcohol consumption (p = 0.053) or physical activity level (p = 0.423).
In the analysis of urinary BPA, BPF, and BPS concentrations among the 2,639 participants, the GMs and GSDs for BPA, BPF, and BPS were 0.993 (4.618) μg/L, 0.178 (3.736) μg/L, and 0.128 (3.704) μg/L, respectively. The GM (GSD) of urinary BPA concentration was 1.031 (4.682) μg/L in the non-MetS group and 0.950 (4.541) μg/L in the MetS group, with no significant difference between the groups (p = 0.170). Similarly, no significant between-group difference was observed for urinary BPS concentration, with GM (GSD) values of 0.125 (3.594) μg/L in the non-MetS group and 0.131 (3.835) μg/L in the MetS group (p = 0.424). In contrast, the GM (GSD) of urinary BPF concentration was 0.169 (3.768) μg/L in the non-MetS group and 0.190 (3.690) μg/L in the MetS group, showing a significantly higher concentration in the MetS group (p = 0.023) (Table 2).
Binary logistic regression analysis was performed to evaluate the association between tertiles of urinary bisphenol concentrations and MetS. Setting the lowest tertile (T1) of each compound as the reference group, the ORs and 95% CIs were estimated.
No significant association was observed between BPA and an increased risk of MetS for either T2 or T3. In model 2, the final adjusted model, the ORs for BPA T2 and T3 were 0.988 (95% CI: 0.750–1.300) and 1.303 (95% CI: 0.965–1.759), respectively.
In contrast, BPF showed a significant positive association with MetS. In the crude model, the ORs for BPF T2 and T3 were 1.370 (95% CI: 1.070–1.754) and 1.436 (95% CI: 1.110–1.857), respectively. This association remained significant in model 1, which was adjusted for age, sex, and urinary creatinine levels, with ORs of 1.332 (95% CI: 1.041–1.704) and 1.521 (95% CI: 1.171–1.975), respectively. In the final model 2, which was further adjusted for alcohol consumption, smoking status, physical activity, and education level, the ORs for BPF T2 and T3 were 1.320 (95% CI: 1.029–1.693) and 1.452 (95% CI: 1.122–1.878), respectively, indicating a significant increase.
For BPS, no significant association was observed in the crude model, but a significant association emerged in the highest tertile (T3) after adjustment. The OR for BPS T3 was 1.383 (95% CI: 1.019–1.877) in model 1 and 1.476 (95% CI: 1.067–2.043) in model 2. In contrast, the association for BPS T2 was not significant in any model (Table 3).
DISCUSSION
This study examined the association between urinary bisphenol levels and MetS in Korean adults using data from the nationwide KoNEHS. The significance of this study lies in its distinction as the first domestic study to assess the association between urinary BPF and BPS concentrations and MetS in Korean adults. Some urinary bisphenol concentrations were significantly associated with higher odds of MetS. Urinary BPF concentrations showed a significant positive association with MetS across the crude model, model 1, and model 2. The urinary BPS concentration exhibited a significant association only in the highest tertile after adjusting for covariates.
Exposure to bisphenols can be broadly categorized into three routes: oral, dermal, and inhalation. In the general population, the primary route of exposure is oral exposure through food and food contact materials.22 Once bisphenols enter the body, they are primarily metabolized in the liver through processes including glucuronidation and sulfation, and are subsequently excreted. Among various bisphenols, BPA has been the most extensively studied bisphenol in humans.23 BPF and BPS are also known to generally follow metabolic and excretion pathways similar to those of BPA. However, experimental and toxicokinetic studies have indicated that BPS and BPF exhibit different conjugation patterns compared to BPA. Specifically, as reported, BPS may lead to increased internal exposure in its unconjugated form due to a lower glucuronidation rate compared to that of BPA.24,25 These disparities in metabolic characteristics have the potential to influence variations in exposure levels and retention patterns among bisphenol analogs. The mechanism by which bisphenols may contribute to MetS is better understood as a complex pathophysiological process involving the interaction of endocrine disruption, adipose tissue dysfunction, changes in insulin secretion and sensitivity, inflammation, and oxidative stress, rather than a single pathway.
Bisphenols have been demonstrated to induce the classical genomic estrogenic responses and non-classical transcriptional regulation via nuclear ERs, ERα and ERβ.26 Furthermore, they have been shown to activate rapid non-genomic signaling through membrane-associated ERs, such as G protein-coupled estrogen receptor (GPER/GPR30), thereby activating kinase cascades, including extracellular signal-regulated kinase/mitogen-activated protein kinase.27 Through these multilayered mechanisms, bisphenols may interact with various estrogen-associated receptors and signaling pathways, potentially altering gene expression related to energy metabolism, fat accumulation, and insulin signaling in key tissues involved in metabolic homeostasis.28,29
In adipose tissue, bisphenols can promote preadipocyte differentiation (adipogenesis) and affect the function of mature adipocytes, thereby inducing fat accumulation.30 Bisphenols may also lead to adipose tissue dysfunction by reducing adiponectin secretion in adipose tissue while increasing the expression of inflammatory cytokines/adipokines, such as interleukin (IL)-6, IL-1β, IL-17A, and tumor necrosis factor-α.31 These alterations extend beyond mere fat accumulation, potentially exacerbating MetS by contributing to chronic low-grade inflammation and insulin resistance.15
Bisphenols can reduce glucose utilization by inducing decreased Akt phosphorylation and impaired glucose transporter type 4–related signaling in skeletal muscle, which may contribute to glucose intolerance and insulin resistance.32 The hyperglycemia and hyperinsulinemia resulting from these metabolic abnormalities increase oxidative stress in the vascular endothelium and reduce the bioavailability of nitric oxide, leading to endothelial dysfunction.33 In addition, they may contribute to the development of dyslipidemia, including elevated triglycerides and reduced HDL, through abnormal gene expression in the liver affecting fatty acid and lipoprotein metabolism.34
The association between bisphenols and MetS has been documented in several previous studies. A study based on National Health and Nutrition Examination Survey (NHANES) data found that among adults in the United States, the group with the highest urinary BPA concentrations had an OR of 1.51 for MetS compared to the group with the lowest concentrations.35 Another study using both NHANES and KoNEHS data investigated the associations between urinary bisphenol concentrations and obesity/metabolic disorders. That study found that high BPA concentrations were associated with reduced HDL cholesterol, increased triglyceride levels, and obesity prevalence in U.S. and Korean adult populations. Furthermore, BPF demonstrated an association with reduced HDL cholesterol and obesity prevalence in adult women in the United States, while BPS exhibited an association with obesity prevalence in adult men in the United States and adult women in South Korea.20 Some in vitro studies employing human adipose-derived stem cells demonstrated that BPF and BPS enhance lipid accumulation and adipogenesis in a dose-dependent manner.36
The findings of this study are consistent with those of previous studies regarding BPF and BPS. Nevertheless, no significant association was found between BPA exposure and the odds of MetS. This discrepancy may be attributable to alterations in the exposure environment resulting from the recent decline in BPA use and the increasing use of alternative bisphenols. Furthermore, considering the short biological half-life and high intra-individual variability of BPA, it is necessary to account for the possibility that a single urine sample may not adequately reflect long-term exposure. Additionally, the inconsistencies in the results may be due to differences in demographic characteristics, lifestyle habits, and sources of exposure between this study and existing studies.
The differing dose-response patterns observed for BPF and BPS may be interpreted in light of differences in the toxicokinetic properties and threshold concentrations of the two compounds. BPF showed a significant association in both T2 and T3, suggesting that its relatively high affinity for ERα may be sufficient to induce receptor-mediated metabolic disruption even at comparatively low exposure levels.37 BPS, in contrast, showed a significant association only in the highest tertile (T3). This pattern is consistent with the non-monotonic dose-response relationship, a characteristic feature widely recognized among EDCs, whereby distinct biological responses can occur at low-to-moderate versus high exposure levels; it is possible that the metabolic disruptive effects of BPS emerge only above a certain threshold concentration. Nevertheless, this mechanistic interpretation is speculative and warrants validation through future experimental studies.
In an exploratory sex-stratified analysis, the association of BPF appeared more pronounced among women, whereas that of BPS appeared more pronounced among men. These patterns are mechanistically consistent with the relatively high ERα affinity of BPF and known sex differences in the toxicokinetics of BPS. However, the sex × bisphenol interaction term was not statistically significant in the final adjusted model, limiting the extent to which these findings can be interpreted as definitive. Future studies with adequate statistical power should systematically verify the associations between bisphenol substitutes and individual components of MetS through pre-specified sex-stratified analyses and interaction tests.
This study has the following limitations. First, this study adopted a cross-sectional design, which makes it difficult to establish the causal direction between bisphenol exposure and MetS. In particular, the possibility of reverse causation cannot be ruled out. Individuals with MetS may consume processed and delivery foods more frequently, and such dietary patterns could increase exposure to bisphenols that can leach from food packaging materials. Therefore, this cross-sectional study alone cannot determine whether the observed association reflects the development of MetS resulting from bisphenol exposure, or increased bisphenol exposure resulting from the lifestyle patterns of individuals with MetS. Long-term prospective cohort studies are needed to overcome this limitation. Second, although it is known that exposure to bisphenols in the general population primarily occurs through diet, this study did not assess dietary factors that could have influenced bisphenol exposure, including the type of food containers used, frequency of plastic product use, frequency of canned food consumption, and total calorie intake. Furthermore, non-dietary exposure sources, such as occupational exposure, have not been reflected. Third, this study has a methodological limitation in that it assessed bisphenol exposure using urine samples taken at a single time point. Spot urine biomonitoring of bisphenols is a widely adopted approach in major national epidemiologic studies, including NHANES, and has been shown to adequately reflect the population-level distribution of average exposure when randomly collected from a large sample.38 However, because bisphenols have a short biological half-life and exhibit substantial diurnal and day-to-day intra-individual variability, a single-time-point urine sample may not fully capture the long-term average exposure relevant to chronic disease development. Such non-differential exposure misclassification would bias association estimates toward the null, suggesting that the significant associations observed between BPF and BPS and MetS in this study may have been conservatively estimated relative to the true associations. Future prospective studies incorporating repeated-measures designs are needed to address this limitation. Fourth, limited data prevented adjustment for additional medications and other environmental chemicals that could influence MetS. Fifth, several previous studies have reported that nonalcoholic fatty liver disease, polycystic ovary syndrome, and hypogonadism are metabolic abnormalities closely associated with insulin resistance and increased cardiovascular disease risk, suggesting the need to incorporate these factors as extended indicators of MetS.39 However, this study defined MetS according to the modified NCEP ATP III criteria, which do not include these factors. Given the possibility that bisphenol exposure may also be associated with these additional indicators, the use of the modified NCEP ATP III criteria to define MetS in this study may have led to an underestimation of the actual association between bisphenol exposure and MetS. Therefore, it will be necessary to evaluate the association between exposure to bisphenols and MetS in future studies by considering these additional indicators. Sixth, the prevalence of MetS observed in this study (46.15%) was higher than a previous nationally representative estimate among Korean adults (33.2%).5 This discrepancy is likely attributable primarily to an increased proportion of participants meeting the glycemic criterion when HbA1c (≥5.7%) was used in place of fasting blood glucose (≥100 mg/dL), with changes in sample composition resulting from the exclusion of 2020 survey data due to the COVID-19 pandemic and differences in age distribution also likely contributing to a lesser extent. The nature of the misclassification arising from the imperfect concordance between HbA1c and fasting blood glucose cannot be determined from the present data alone. If this misclassification is non-differential with respect to bisphenol exposure, the association estimates would be biased toward the null, potentially leading to an underestimation of the true association. Conversely, if bisphenols affect oxidative stress or erythrocyte metabolism in a manner that causes the degree of misclassification to vary by exposure level—that is, differential misclassification—the direction of bias would be difficult to predict. Therefore, although the higher MetS prevalence observed in this study does not directly suggest an overestimation of the association with bisphenol exposure, the possibility of bias due to misclassification cannot be excluded. Future studies using data with measured fasting blood glucose are needed to confirm the reproducibility of these findings.
CONCLUSIONS
This study analyzed the association between urinary bisphenol concentrations and MetS in a nationally representative sample of Korean adults using raw data from KoNEHS. Urinary BPF and BPS concentrations showed significant positive associations with MetS. Notably, the pattern of bisphenol exposure among Korean adults appears to be shifting from BPA toward alternative bisphenols, including BPF and BPS.40 In this context, this study is meaningful in suggesting that BPA alternatives, such as BPF and BPS, may also be associated with MetS in humans. Furthermore, with the gradual increase in exposure to various BPA analogs, long-term prospective studies involving the general population remain necessary to assess the health effects of these substances. The findings of this study may serve as basic evidence for broadening our understanding of the health effects of bisphenols, and they are also expected to inform future discussions about environmental health policies.
Abbreviations
BMI
body mass index
BPA
bisphenol A
BPF
bisphenol F
BPS
bisphenol S
CI
confidence interval
COVID-19
coronavirus disease 2019
EDC
endocrine-disrupting chemical
ER
estrogen receptor
GM
geometric mean
GPER
G protein-coupled estrogen receptor
GSD
geometric standard deviation
HbA1c
glycated hemoglobin
HDL
high-density lipoprotein
IL
interleukin
KoNEHS
Korean National Environmental Health Survey
MDL
method detection limit
MetS
metabolic syndrome
NCEP ATP III
National Cholesterol Education Program Adult Treatment Panel III
NHANES
National Health and Nutrition Examination Survey
OR
odds ratio
-
Competing interests
The authors declare that they have no competing interests.
-
Author contributions
Conceptualization: Jae CH. Data curation: Shin YH, Park YT. Formal analysis: Jae CH. Funding acquisition: Shin YH. Investigation: Jae CH, Park YT, Kang DY. Methodology: Shin YH, Chae CH. Software: Jae CH. Validation: Shin YH, Kim CW, Park HO. Visualization: Jae CH. Writing - original draft: Jae CH. Writing - review & editing: Jae CH, Shin YH, Chae CH, Kim CW, Park HO.
NOTES
Fig. 1.
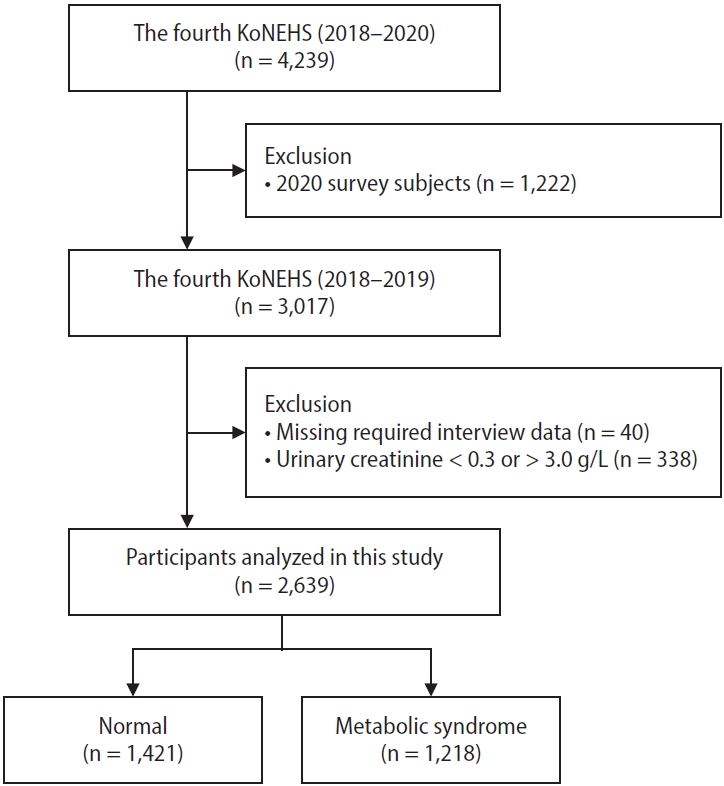
Selection of analytic samples in this study. KoNEHS: Korean National Environmental Health Survey.
Table 1.
General characteristics of the study population
| Variable | Unweighted sample size (weighted %) | p-valuea | ||
|---|---|---|---|---|
| Total (n = 2,639) | Non-MetS (n = 1,421) | MetS (n = 1,218) | ||
| Age (years) | <0.001 | |||
| 19–39 | 547 (34.1) | 424 (45.2) | 123 (18.3) | |
| 40–59 | 1,091 (39.0) | 627 (36.9) | 464 (42.0) | |
| ≥60 | 1,001 (27.0) | 370 (17.9) | 631 (39.7) | |
| Sex | 0.001 | |||
| Male | 1,219 (51.8) | 596 (47.8) | 623 (57.5) | |
| Female | 1,420 (48.2) | 825 (52.2) | 595 (42.5) | |
| BMI (kg/m2) | <0.001 | |||
| Normal | 1,374 (52.7) | 1,009 (70.9) | 365 (27.0) | |
| Overweight/obeseb | 1,265 (47.3) | 412 (29.1) | 853 (73.0) | |
| Alcohol consumption | 0.053 | |||
| No | 544 (18.8) | 259 (17.3) | 285 (20.9) | |
| <1 time/monthc | 667 (23.0) | 334 (21.0) | 333 (25.7) | |
| ≥1 time/month | 1,428 (58.3) | 828 (61.7) | 600 (53.4) | |
| Smoking status | <0.001 | |||
| No | 1,644 (61.0) | 957 (65.9) | 687 (54.0) | |
| Former | 559 (19.2) | 265 (17.4) | 294 (21.7) | |
| Current | 436 (19.9) | 199 (16.7) | 237 (24.3) | |
| Physical activity | 0.423 | |||
| No | 1,405 (53.4) | 744 (52.4) | 661 (54.8) | |
| Intermediated | 182 (6.5) | 86 (6.1) | 96 (7.0) | |
| Vigorous | 1,052 (40.1) | 591 (41.5) | 461 (38.2) | |
| Education | <0.001 | |||
| Less than high school | 413 (10.9) | 136 (6.1) | 277 (17.7) | |
| High school graduate | 1,094 (36.4) | 522 (29.5) | 572 (46.0) | |
| University or higher | 1,132 (52.7) | 763 (64.4) | 369 (36.2) | |
Values are presented as number (weighted %), where n represents the unweighted sample size.
aThe p-value calculated by chi-square test (categorical);
bBody mass index (BMI) ≥25 kg/m² was classified as overweight/obese according to the World Health Organization Asia-Pacific criteria;
c’Less than once a month’ was defined as alcohol consumption on fewer than one occasion per month;
dPhysical activity that did not induce sweating.
Table 2.
Distribution of urinary bisphenol levels (μg/L) in the study population
| Urinary bisphenol | Unweighted sample size | p-valuea | ||
|---|---|---|---|---|
| Total (n = 2,639) | Non-MetS (n = 1,421) | MetS (n = 1,218) | ||
| BPA | 0.170 | |||
| GM (GSD) | 0.993 (4.618) | 1.031 (4.682) | 0.950 (4.541) | |
| T1 | 0.021–0.727 | 0.021–0.756 | 0.021–0.711 | |
| T2 | 0.727–1.887 | 0.756–1.936 | 0.711–1.847 | |
| T3 | 1.887–128.040 | 1.936–128.040 | 1.847–94.436 | |
| BPF | 0.023 | |||
| GM (GSD) | 0.178 (3.736) | 0.169 (3.768) | 0.190 (3.690) | |
| T1 | 0.025–0.075 | 0.025–0.059 | 0.025–0.091 | |
| T2 | 0.075–0.288 | 0.059–0.273 | 0.091–0.310 | |
| T3 | 0.288–142.477 | 0.273–142.477 | 0.310–139.320 | |
| BPS | 0.424 | |||
| GM (GSD) | 0.128 (3.704) | 0.125 (3.594) | 0.131 (3.835) | |
| T1 | 0.016–0.075 | 0.016–0.075 | 0.016–0.075 | |
| T2 | 0.075–0.199 | 0.075–0.193 | 0.075–0.205 | |
| T3 | 0.199–31.813 | 0.193–13.816 | 0.205–31.813 | |
Table 3.
Risk of metabolic syndrome by tertiles of urinary bisphenols using binary logistic regression
| Urinary bisphenol | Crude | Model 1a | Model 2b | |||
|---|---|---|---|---|---|---|
| OR | 95% CI | OR | 95% CI | OR | 95% CI | |
| BPA | ||||||
| T1 | 1 | Ref | 1 | Ref | 1 | Ref |
| T2 | 0.857 | 0.642–1.143 | 0.914 | 0.690–1.211 | 0.988 | 0.750–1.300 |
| T3 | 0.955 | 0.696–1.310 | 1.219 | 0.898–1.655 | 1.303 | 0.965–1.759 |
| BPF | ||||||
| T1 | 1 | Ref | 1 | Ref | 1 | Ref |
| T2 | 1.370 | 1.070–1.754 | 1.332 | 1.041–1.704 | 1.320 | 1.029–1.693 |
| T3 | 1.436 | 1.110–1.857 | 1.521 | 1.171–1.975 | 1.452 | 1.122–1.878 |
| BPS | ||||||
| T1 | 1 | Ref | 1 | Ref | 1 | Ref |
| T2 | 1.134 | 0.870–1.478 | 1.173 | 0.896–1.536 | 1.258 | 0.976–1.621 |
| T3 | 1.195 | 0.950–1.504 | 1.383 | 1.019–1.877 | 1.476 | 1.067–2.043 |
Crude: Urinary bisphenol, metabolic syndrome.
OR: odds ratio; CI: confidence interval; BPA: bisphenol A; T: tertile; BPF: bisphenol F; BPS: bisphenol S.
aCrude + adjusted for age (group), sex, urinary creatinine levels;
bModel 1 + adjusted for alcohol consumption, smoking status, physical activity, education.
- 1. Swarup S, Ahmed I, Grigorova Y, Zeltser R. Metabolic Syndrome. StatPearls. Treasure Island, FL: StatPearls Publishing Copyright; 2026.
- 2. Asrih M, Jornayvaz FR. Metabolic syndrome and nonalcoholic fatty liver disease: is insulin resistance the link? Mol Cell Endocrinol 2015;418 Pt 1:55–65.ArticlePubMed
- 3. Singh AK, Kari JA. Metabolic syndrome and chronic kidney disease. Curr Opin Nephrol Hypertens 2013;22(2):198–203.ArticlePubMed
- 4. Ranasinghe P, Mathangasinghe Y, Jayawardena R, Hills AP, Misra A. Prevalence and trends of metabolic syndrome among adults in the asia-pacific region: a systematic review. BMC Public Health 2017;17(1):101.ArticlePubMedPMCPDF
- 5. Park D, Shin MJ, Despres JP, Eckel RH, Tuomilehto J, Lim S. 20-Year trends in metabolic syndrome among Korean adults from 2001 to 2020. JACC Asia 2023;3(3):491–502.ArticlePubMedPMC
- 6. Haverinen E, Fernandez MF, Mustieles V, Tolonen H. Metabolic syndrome and endocrine disrupting chemicals: an overview of exposure and health effects. Int J Environ Res Public Health 2021;18(24):13047.Article
- 7. Yilmaz B, Terekeci H, Sandal S, Kelestimur F. Endocrine disrupting chemicals: exposure, effects on human health, mechanism of action, models for testing and strategies for prevention. Rev Endocr Metab Disord 2020;21(1):127–47.ArticlePubMedPDF
- 8. Moreman J, Lee O, Trznadel M, David A, Kudoh T, Tyler CR. Acute toxicity, teratogenic, and estrogenic effects of bisphenol A and its alternative replacements bisphenol S, bisphenol F, and bisphenol AF in zebrafish embryo-larvae. Environ Sci Technol 2017;51(21):12796–805.ArticlePubMed
- 9. Vandenberg LN, Hauser R, Marcus M, Olea N, Welshons WV. Human exposure to bisphenol A (BPA). Reprod Toxicol 2007;24(2):139–77.ArticlePubMed
- 10. Calafat AM, Ye X, Wong LY, Reidy JA, Needham LL. Exposure of the U.S. population to bisphenol A and 4-tertiary-octylphenol: 2003-2004. Environ Health Perspect 2008;116(1):39–44.ArticlePubMedPMC
- 11. Moon MK. Concern about the safety of bisphenol A substitutes. Diabetes Metab J 2019;43(1):46–8.ArticlePubMedPMCPDF
- 12. Rochester JR. Bisphenol A and human health: a review of the literature. Reprod Toxicol 2013;42:132–55.ArticlePubMed
- 13. Delfosse V, Grimaldi M, Pons JL, Boulahtouf A, le Maire A, Cavailles V, et al. Structural and mechanistic insights into bisphenols action provide guidelines for risk assessment and discovery of bisphenol A substitutes. Proc Natl Acad Sci U S A 2012;109(37):14930–5.ArticlePubMedPMC
- 14. Ohlstein JF, Strong AL, McLachlan JA, Gimble JM, Burow ME, Bunnell BA. Bisphenol A enhances adipogenic differentiation of human adipose stromal/stem cells. J Mol Endocrinol 2014;53(3):345–53.ArticlePubMedPMC
- 15. Ben-Jonathan N, Hugo ER, Brandebourg TD. Effects of bisphenol A on adipokine release from human adipose tissue: implications for the metabolic syndrome. Mol Cell Endocrinol 2009;304(1-2):49–54.ArticlePubMedPMC
- 16. Pelch K, Wignall JA, Goldstone AE, Ross PK, Blain RB, Shapiro AJ, et al. A scoping review of the health and toxicological activity of bisphenol A (BPA) structural analogues and functional alternatives. Toxicology 2019;424:152235.ArticlePubMed
- 17. Kim HJ, Kang DR, Kim JY, Kim W, Jeong YW, Chun KH. Metabolic syndrome fact sheet 2024: executive report. Cardiometab Syndr J 2024;4(2):70–80.ArticlePDF
- 18. Cavero-Redondo I, Martinez-Vizcaino V, Alvarez-Bueno C, Agudo-Conde C, Lugones-Sanchez C, Garcia-Ortiz L. Metabolic syndrome including glycated hemoglobin A1c in adults: is it time to change? J Clin Med 2019;8(12):2090.ArticlePubMedPMC
- 19. Li P, Jiang R, Li L, Li X, Liu C, Xu W, et al. Usefulness of hemoglobin A(1c) as a criterion to define metabolic syndrome in nondiabetic Chinese adolescents. J Investig Med 2013;61(3):586–92.ArticlePubMedPDF
- 20. Choi JY, Lee J, Huh DA, Moon KW. Urinary bisphenol concentrations and its association with metabolic disorders in the US and Korean populations. Environ Pollut 2022;295:118679.ArticlePubMed
- 21. Zhang W, Xia W, Liu W, Li X, Hu J, Zhang B, et al. Exposure to bisphenol a substitutes and gestational diabetes mellitus: A prospective cohort study in China. Front Endocrinol (Lausanne) 2019;10:262.ArticlePubMedPMC
- 22. Manzoor MF, Tariq T, Fatima B, Sahar A, Tariq F, Munir S, et al. An insight into bisphenol A, food exposure and its adverse effects on health: a review. Front Nutr 2022;9:1047827.ArticlePubMedPMC
- 23. Thayer KA, Doerge DR, Hunt D, Schurman SH, Twaddle NC, Churchwell MI, et al. Pharmacokinetics of bisphenol A in humans following a single oral administration. Environ Int 2015;83:107–15.ArticlePubMedPMC
- 24. Karrer C, Roiss T, von Goetz N, Gramec Skledar D, Peterlin Masic L, Hungerbuhler K. Physiologically based pharmacokinetic (PBPK) modeling of the bisphenols BPA, BPS, BPF, and BPAF with new experimental metabolic parameters: comparing the pharmacokinetic behavior of BPA with its substitutes. Environ Health Perspect 2018;126(7):077002.ArticlePubMedPMC
- 25. Khmiri I, Cote J, Mantha M, Khemiri R, Lacroix M, Gely C, et al. Toxicokinetics of bisphenol-S and its glucuronide in plasma and urine following oral and dermal exposure in volunteers for the interpretation of biomonitoring data. Environ Int 2020;138:105644.ArticlePubMed
- 26. Shanle EK, Xu W. Endocrine disrupting chemicals targeting estrogen receptor signaling: identification and mechanisms of action. Chem Res Toxicol 2011;24(1):6–19.ArticlePubMed
- 27. Pupo M, Pisano A, Lappano R, Santolla MF, De Francesco EM, Abonante S, et al. Bisphenol A induces gene expression changes and proliferative effects through GPER in breast cancer cells and cancer-associated fibroblasts. Environ Health Perspect 2012;120(8):1177–82.ArticlePubMedPMC
- 28. Moon MK, Jeong IK, Oh TJ, Ahn HY, Kim HH, Park YJ, et al. Long-term oral exposure to bisphenol A induces glucose intolerance and insulin resistance. J Endocrinol 2015;226(1):35–42.ArticlePubMed
- 29. Li C, Shen N, Yang S, Wang HL. Effects of BPA exposure and recovery on the expression of genes involved in the hepatic lipid metabolism in male mice. Toxics 2023;11(9):775.ArticlePubMedPMC
- 30. Menale C, Piccolo MT, Cirillo G, Calogero RA, Papparella A, Mita L, et al. Bisphenol A effects on gene expression in adipocytes from children: association with metabolic disorders. J Mol Endocrinol 2015;54(3):289–303.ArticlePubMed
- 31. Gonzalez-Casanova JE, Bermudez V, Caro Fuentes NJ, Angarita LC, Caicedo NH, Rivas Munoz J, et al. New evidence on BPA's role in adipose tissue development of proinflammatory processes and its relationship with obesity. Int J Mol Sci 2023;24(9):8231.ArticlePubMedPMC
- 32. Indumathi D, Jayashree S, Selvaraj J, Sathish S, Mayilvanan C, Akilavalli N, et al. Effect of bisphenol-A on insulin signal transduction and glucose oxidation in skeletal muscle of adult male albino rat. Hum Exp Toxicol 2013;32(9):960–71.ArticlePubMedPDF
- 33. Meza CA, La Favor JD, Kim DH, Hickner RC. Endothelial dysfunction: is there a hyperglycemia-induced imbalance of NOX and NOS? Int J Mol Sci 2019;20(15):3775.ArticlePubMedPMC
- 34. Bjornstad P, Eckel RH. Pathogenesis of lipid disorders in insulin resistance: a brief review. Curr Diab Rep 2018;18(12):127.ArticlePubMedPMCPDF
- 35. Teppala S, Madhavan S, Shankar A. Bisphenol A and metabolic syndrome: results from NHANES. Int J Endocrinol 2012;2012:598180.ArticlePubMedPMCPDF
- 36. Reina-Perez I, Olivas-Martinez A, Mustieles V, Ruiz-Ojeda FJ, Molina-Molina JM, Olea N, et al. Bisphenol F and bisphenol S promote lipid accumulation and adipogenesis in human adipose-derived stem cells. Food Chem Toxicol 2021;152:112216.ArticlePubMed
- 37. Rochester JR, Bolden AL. Bisphenol S and F: a systematic review and comparison of the hormonal activity of bisphenol A substitutes. Environ Health Perspect 2015;123(7):643–50.ArticlePubMedPMC
- 38. Ye X, Wong LY, Bishop AM, Calafat AM. Variability of urinary concentrations of bisphenol A in spot samples, first morning voids, and 24-hour collections. Environ Health Perspect 2011;119(7):983–8.ArticlePubMedPMC
- 39. Cornier MA, Dabelea D, Hernandez TL, Lindstrom RC, Steig AJ, Stob NR, et al. The metabolic syndrome. Endocr Rev 2008;29(7):777–822.ArticlePubMedPMC
- 40. Kang J, Kang H, Choi YH. Changes of urinary bisphenol A and alternatives in Korea 2015-2020 and environmental disparities by socioeconomic status. Environ Res 2025;285(Pt 1):122307.ArticlePubMed
REFERENCES
Figure & Data
REFERENCES
Citations
Citations to this article as recorded by 
 Cite
 XML Download
- Figure
-
- Related articles
-
- Association between organochlorine pesticides, polychlorinated biphenyls mixture and cardiometabolic outcomes: findings from the Korean National Environmental Health Survey (KoNEHS)
- Association between seafood consumption and urinary bisphenol concentrations in Korean adults: findings from the Korean National Environmental Health Survey (KoNEHS 2018–2020)
- Association between seafood consumption and serum polyfluoroalkyl substance concentrations among Korean adolescents: the Korean National Environmental Health Survey (KoNEHS) cycle 5, 2021–2023
- Association between delivery-food consumption frequency and urinary bisphenol concentrations among Korean adults: a nationally representative study (Korean National Environmental Health Survey cycle 5, 2021–2023)
- The association between commute time and both presenteeism and absenteeism: a cross-sectional analysis of the 6th Korean Working Conditions Survey
Association between urinary bisphenol levels and metabolic syndrome in Korean adults: a cross-sectional study using the fourth Korean National Environmental Health Survey
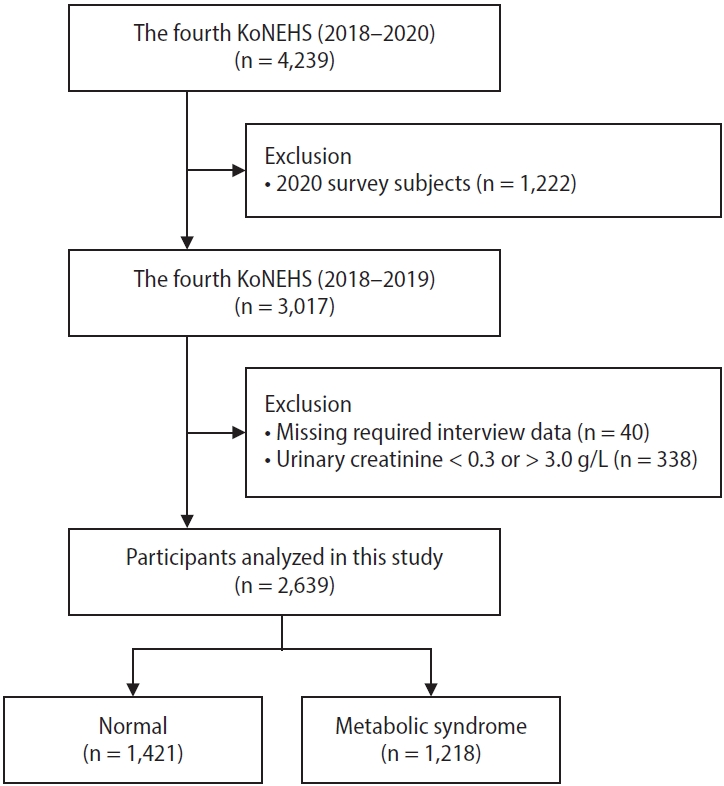
Fig. 1. Selection of analytic samples in this study. KoNEHS: Korean National Environmental Health Survey.
Fig. 1.
Association between urinary bisphenol levels and metabolic syndrome in Korean adults: a cross-sectional study using the fourth Korean National Environmental Health Survey
| Variable | Unweighted sample size (weighted %) | p-value |
||
|---|---|---|---|---|
| Total (n = 2,639) | Non-MetS (n = 1,421) | MetS (n = 1,218) | ||
| Age (years) | <0.001 | |||
| 19–39 | 547 (34.1) | 424 (45.2) | 123 (18.3) | |
| 40–59 | 1,091 (39.0) | 627 (36.9) | 464 (42.0) | |
| ≥60 | 1,001 (27.0) | 370 (17.9) | 631 (39.7) | |
| Sex | 0.001 | |||
| Male | 1,219 (51.8) | 596 (47.8) | 623 (57.5) | |
| Female | 1,420 (48.2) | 825 (52.2) | 595 (42.5) | |
| BMI (kg/m2) | <0.001 | |||
| Normal | 1,374 (52.7) | 1,009 (70.9) | 365 (27.0) | |
| Overweight/obese |
1,265 (47.3) | 412 (29.1) | 853 (73.0) | |
| Alcohol consumption | 0.053 | |||
| No | 544 (18.8) | 259 (17.3) | 285 (20.9) | |
| <1 time/month |
667 (23.0) | 334 (21.0) | 333 (25.7) | |
| ≥1 time/month | 1,428 (58.3) | 828 (61.7) | 600 (53.4) | |
| Smoking status | <0.001 | |||
| No | 1,644 (61.0) | 957 (65.9) | 687 (54.0) | |
| Former | 559 (19.2) | 265 (17.4) | 294 (21.7) | |
| Current | 436 (19.9) | 199 (16.7) | 237 (24.3) | |
| Physical activity | 0.423 | |||
| No | 1,405 (53.4) | 744 (52.4) | 661 (54.8) | |
| Intermediate |
182 (6.5) | 86 (6.1) | 96 (7.0) | |
| Vigorous | 1,052 (40.1) | 591 (41.5) | 461 (38.2) | |
| Education | <0.001 | |||
| Less than high school | 413 (10.9) | 136 (6.1) | 277 (17.7) | |
| High school graduate | 1,094 (36.4) | 522 (29.5) | 572 (46.0) | |
| University or higher | 1,132 (52.7) | 763 (64.4) | 369 (36.2) | |
| Urinary bisphenol | Unweighted sample size | p-value |
||
|---|---|---|---|---|
| Total (n = 2,639) | Non-MetS (n = 1,421) | MetS (n = 1,218) | ||
| BPA | 0.170 | |||
| GM (GSD) | 0.993 (4.618) | 1.031 (4.682) | 0.950 (4.541) | |
| T1 | 0.021–0.727 | 0.021–0.756 | 0.021–0.711 | |
| T2 | 0.727–1.887 | 0.756–1.936 | 0.711–1.847 | |
| T3 | 1.887–128.040 | 1.936–128.040 | 1.847–94.436 | |
| BPF | 0.023 | |||
| GM (GSD) | 0.178 (3.736) | 0.169 (3.768) | 0.190 (3.690) | |
| T1 | 0.025–0.075 | 0.025–0.059 | 0.025–0.091 | |
| T2 | 0.075–0.288 | 0.059–0.273 | 0.091–0.310 | |
| T3 | 0.288–142.477 | 0.273–142.477 | 0.310–139.320 | |
| BPS | 0.424 | |||
| GM (GSD) | 0.128 (3.704) | 0.125 (3.594) | 0.131 (3.835) | |
| T1 | 0.016–0.075 | 0.016–0.075 | 0.016–0.075 | |
| T2 | 0.075–0.199 | 0.075–0.193 | 0.075–0.205 | |
| T3 | 0.199–31.813 | 0.193–13.816 | 0.205–31.813 | |
| Urinary bisphenol | Crude | Model 1 |
Model 2 |
|||
|---|---|---|---|---|---|---|
| OR | 95% CI | OR | 95% CI | OR | 95% CI | |
| BPA | ||||||
| T1 | 1 | Ref | 1 | Ref | 1 | Ref |
| T2 | 0.857 | 0.642–1.143 | 0.914 | 0.690–1.211 | 0.988 | 0.750–1.300 |
| T3 | 0.955 | 0.696–1.310 | 1.219 | 0.898–1.655 | 1.303 | 0.965–1.759 |
| BPF | ||||||
| T1 | 1 | Ref | 1 | Ref | 1 | Ref |
| T2 | 1.370 | 1.070–1.754 | 1.332 | 1.041–1.704 | 1.320 | 1.029–1.693 |
| T3 | 1.436 | 1.110–1.857 | 1.521 | 1.171–1.975 | 1.452 | 1.122–1.878 |
| BPS | ||||||
| T1 | 1 | Ref | 1 | Ref | 1 | Ref |
| T2 | 1.134 | 0.870–1.478 | 1.173 | 0.896–1.536 | 1.258 | 0.976–1.621 |
| T3 | 1.195 | 0.950–1.504 | 1.383 | 1.019–1.877 | 1.476 | 1.067–2.043 |
Table 1. General characteristics of the study population
Values are presented as number (weighted %), where n represents the unweighted sample size. The Body mass index (BMI) ≥25 kg/m² was classified as overweight/obese according to the World Health Organization Asia-Pacific criteria; ’Less than once a month’ was defined as alcohol consumption on fewer than one occasion per month; Physical activity that did not induce sweating.
Table 2. Distribution of urinary bisphenol levels (μg/L) in the study population
MetS: metabolic syndrome; BPA: bisphenol A; GM: geometric mean; GSD: geometric standard deviation; T, tertile; BPF: bisphenol F; BPS: bisphenol S. The
Table 3. Risk of metabolic syndrome by tertiles of urinary bisphenols using binary logistic regression
Crude: Urinary bisphenol, metabolic syndrome. OR: odds ratio; CI: confidence interval; BPA: bisphenol A; T: tertile; BPF: bisphenol F; BPS: bisphenol S. Crude + adjusted for age (group), sex, urinary creatinine levels; Model 1 + adjusted for alcohol consumption, smoking status, physical activity, education.


